
This web page was created programmatically, to learn the article in its unique location you may go to the hyperlink bellow:
https://journals.plos.org/plosmedicine/article%3Fid%3D10.1371/journal.pmed.1005043
and if you wish to take away this text from our web site please contact us
Abstract
Background
Type 2 diabetes incidence stays excessive amongst older adults and contributes considerably to morbidity and healthcare burden. Most proof supporting diabetes prevention derives from intensive life-style interventions concentrating on high-risk people beneath managed trial situations. The effectiveness of low-intensity, population-based prevention applications embedded in routine care stays unsure. We evaluated whether or not participation in a complete well being evaluation and counseling program was related to diminished incidence of diabetes in older adults.
Methods and findings
We carried out a population-based matched cohort research together with 70-year-old residents of Umeå municipality, Sweden, enrolled between 2012 and 2022 and adopted via December 2022. The intervention consisted of a complete well being evaluation adopted by individualized motivational counseling, with out structured long-term follow-up. Participants have been matched 1:10 to controls from the overall Swedish inhabitants by start yr, intercourse, and academic degree. Individuals with prevalent diabetes have been excluded. The main final result was incident diabetes, outlined as a primary recorded analysis in specialist care and/or first allotted glucose-lowering medicine, recognized via nationwide well being and prescription registers.
In complete, 6,018 members and 57,543 matched controls have been included. During a imply follow-up of 4.9 years (normal deviation 2.9) within the intervention cohort and 4.8 years (normal deviation 2.9) within the management cohort, diabetes occurred in 335 (5.6%) members and three,919 (6.8%) controls. Participation was related to a decrease danger of incident diabetes (adjusted hazard ratio 0.76; 95% confidence interval [0.68,0.85]; p < 0.001). The affiliation remained steady over time. The absolute danger discount was 1.46 share factors (95% confidence interval [0.91,1.98]; p < 0.001) at 5 years and three.42 share factors (95% confidence interval [2.13,4.75]; p < 0.001) at 10 years. Results have been broadly constant throughout the examined subgroups. The observational research design limits certainty relating to the intervention’s position within the noticed affiliation, and voluntary participation in this system might have launched choice bias, healthy-volunteer impact, and residual confounding.
Conclusions
In this population-based cohort research, participation in a low-intensity preventive well being program delivered in routine care was related to a decrease incidence of diabetes amongst older adults. However, the observational research design limits proof on the intervention’s position within the noticed affiliation, and extra sturdy proof is required. Nevertheless, these findings recommend that scalable, population-wide prevention methods might complement intensive high-risk approaches in addressing diabetes in getting older populations.
Author abstract
Why was this research carried out?
- Type 2 diabetes is widespread in older adults and contributes considerably to morbidity and healthcare prices.
- Most proof for diabetes prevention comes from intensive life-style applications concentrating on chosen high-risk people in scientific trials.
- It stays unclear whether or not low-intensity, population-based prevention applications delivered in routine healthcare settings can cut back diabetes danger within the normal older inhabitants.
What did the researchers do and discover?
- We carried out a population-based matched cohort research together with 6,018 members in a preventive well being evaluation and counseling program and 57,543 matched controls.
- Participants have been 70-year-old residents of Umeå municipality, Sweden, free from diabetes at baseline.
- During a imply follow-up of 4.8 years, participation in this system was related to a 24% decrease danger of creating diabetes.
- The absolute distinction in diabetes danger between teams elevated over time and was constant throughout most examined subgroups.
What do these findings imply?
- In this real-world setting, participation in a low-intensity preventive well being program was related to decrease diabetes incidence amongst older adults.
- The findings recommend that scalable prevention methods embedded in routine care might contribute to lowering diabetes burden on the inhabitants degree, the place even modest reductions in particular person danger might translate into substantial public well being advantages.
- The observational research design doesn’t enable causal conclusions, and voluntary participation might have resulted in a more healthy group of members than non-participants.
Citation: Bergman E, Nordström A, Nyberg L, Nordström P (2026) Association of a a number of danger issue evaluation and intervention program with danger of diabetes: A population-based matched cohort research. PLoS Med 23(9):
e1005043.
https://doi.org/10.1371/journal.pmed.1005043
Academic Editor: Andre P. Kengne, South African Medical Research Council, SOUTH AFRICA
Received: March 14, 2026; Accepted: September 10, 2026; Published: September 21, 2026
Copyright: © 2026 Bergman et al. This is an open entry article distributed beneath the phrases of the Creative Commons Attribution License, which allows unrestricted use, distribution, and copy in any medium, offered the unique writer and supply are credited.
Data Availability: The individual-level information underlying this research can’t be made publicly obtainable or transferred immediately by the authors as a result of they include delicate private info and are topic to the European Union General Data Protection Regulation, Swedish information safety and confidentiality laws, moral approval, and data-use agreements. Eligible researchers might apply individually to the related information custodians. Applications typically require an eligible analysis establishment, an outlined analysis venture, specification of the requested inhabitants and variables, related moral approval, and approval following authorized and confidentiality evaluation by the respective information custodian. Access just isn’t assured. Health-register information could be requested from the Swedish National Board of Health and Welfare at ([email protected]). Sociodemographic microdata could be requested from Statistics Sweden at ([email protected]). Requests regarding entry to the HAI analysis information must be submitted to the Office of the Registrar at Uppsala University ([email protected]). The authors will not be permitted to redistribute the linked individual-level dataset and had no particular entry privileges unavailable to different eligible researchers. The code used for the statistical analyses and creation of figures is out there from and has been completely archived in Zenodo with the URL: https://doi.org/10.5281/zenodo.21820677, and DOI: https://doi.org/10.5281/zenodo.21820677. The code is offered with out the underlying individual-level information, which have to be requested individually as described above.
Funding: This work was supported by a grant from King Gustaf V and Queen Victoria’s Foundation (URL: https://frimurarestiftelsen.se/) awarded to PN. The Foundation doesn’t assign grant numbers to its awards. The funder had no position in research design, information assortment and evaluation, resolution to publish, or preparation of the manuscript. The writer acquired no wage help from the funder.
Competing pursuits: The authors have declared that no competing pursuits exist.
Abbreviations:
CI,
confidence interval; CVD,
heart problems; DPS,
Diabetes Prevention Study; HAI,
Healthy Ageing Initiative; HR,
hazard ratio; PAF,
Population attributable fraction; SD,
normal deviation
Introduction
Diabetes mellitus is a significant public well being problem and is extremely prevalent amongst older adults [1]. It contributes considerably to cardiovascular morbidity, practical decline, and healthcare utilization worldwide [2–4]. In Sweden and lots of different international locations [5], diabetes incidence will increase with age earlier than plateauing within the oldest age teams [6]. Preventing diabetes in getting older populations is due to this fact an vital scientific and public well being precedence.
Strong proof helps life-style modification for diabetes prevention, primarily from randomized managed trials concentrating on people at elevated danger via intensive, structured applications [7–11]. Although these interventions have demonstrated substantial reductions in diabetes incidence beneath managed situations, their depth, useful resource necessities, and selective inclusion standards might restrict scalability and sustainability in routine healthcare setting [12–14]. Whether lower-intensity, population-based prevention methods embedded in routine care can affect diabetes incidence within the normal older inhabitants stays unsure.
Population-wide preventive initiatives carried out in European and Nordic settings have reported enhancements in life-style behaviors and cardiometabolic danger profiles [15–18]. However, proof relating to their affiliation with exhausting scientific outcomes akin to incident diabetes is proscribed, and older adults are often underrepresented [15]. Moreover, little is thought about whether or not potential associations are constant throughout demographic and scientific subgroups in real-world healthcare contexts [19].
The Healthy Ageing Initiative (HAI) is a population-wide preventive well being program supplied to all 70-year-olds inside an outlined Swedish healthcare area [20]. The program features a complete well being evaluation adopted by individualized motivational counseling delivered inside routine care, with out structured long-term follow-up. Previous analyses have proven that participation on this program was related to diminished heart problems (CVD) incidence [21]. Whether participation can be related to diminished diabetes incidence has not been evaluated. Using a population-based matched cohort design with nationwide register follow-up, we examined whether or not participation on this low-intensity, routine-care prevention program was related to incident diabetes amongst older adults. We additionally assessed whether or not any noticed affiliation was constant throughout key baseline traits.
Methods
Study design and setting
We carried out a population-based matched cohort research analyzing the affiliation between participation within the HAI, a main prevention program in Umeå municipality, Sweden [20], and incident diabetes. Participants in this system have been matched to controls from the overall Swedish inhabitants. Follow-up was carried out via linkage to nationwide registers, together with the National Patient Register, the Prescribed Drug Register, and the Cause of Death Register [22–24], which offer near-complete nationwide protection of diagnoses, allotted drugs, and mortality. The research interval spanned from June 1, 2012, to December 31, 2022. The research was carried out and reported in accordance with Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) tips (S1 Checklist).
Healthy Ageing Initiative cohort.
The intervention cohort comprised 54% of 70-year-old residents invited inside the municipality in the course of the research interval. Participation was open to all eligible people, with no exclusion standards utilized. The program included two structured well being evaluation visits carried out inside routine care, throughout which life-style elements and cardiometabolic danger markers have been evaluated. It was designed as a practical, low-intensity program that may very well be carried out in routine scientific follow to focus on the key modifiable danger elements for CVD and diabetes at a inhabitants degree. Participants acquired individualized suggestions and motivational counseling aimed toward selling life-style modifications related to cardiovascular and metabolic illness prevention. No structured long-term follow-up was offered inside the program, and members subsequently returned to peculiar care. Individuals with findings suggestive of undiagnosed situations have been suggested to seek the advice of their normal practitioner. An in depth description of this system is offered in S1 Appendix, and comparable descriptions have beforehand been revealed [21,25]. The members included in this system have been typically more healthy, with a decrease prevalence of CVD and diabetes, than Umeå residents who didn’t take part [21].
Control cohort.
A management cohort was drawn from the overall Swedish inhabitants by Statistics Sweden and individually matched 1:10 to HAI members precisely on start yr, intercourse, and academic degree [26]. Controls have been required to be alive and freed from diabetes on the index date equivalent to their matched participant and have been assigned the identical index date to make sure comparable follow-up time.
Exclusion standards.
Individuals in each cohorts have been excluded if they’d prevalent diabetes at baseline, outlined as a recorded analysis of diabetes (International Statistical Classification of Diseases and Related Health Problems, tenth Revision, ICD-10 codes E10 and E11) within the National Patient Register or a allotted prescription of glucose-lowering medicine (Anatomical Therapeutic Chemical Classification System, ATC code A10) earlier than or on the index date. Individuals with lacking information on matching variables have been additionally excluded.
Outcome definition
The main final result was incident diabetes throughout follow-up. Incident instances have been recognized via nationwide register linkage to the National Patient Register and the Prescribed Drug Register. Diabetes was outlined as a primary recorded analysis in specialised inpatient or outpatient care (ICD-10 code E11) or a primary allotted prescription of glucose-lowering medicine (ATC code A10), whichever occurred first. The date of the primary qualifying analysis or prescription was used because the occasion date. Participants have been censored at demise, recognized via the Cause of Death Register, or on the finish of follow-up.
Covariates
Baseline covariates have been specified previous to information evaluation, based mostly on subject-matter information, and the provision of persistently recorded variables within the nationwide registers. Age, intercourse, and academic degree have been accounted for via matching. Additional covariates have been chosen to seize baseline variations in cardiometabolic morbidity, total well being and practical standing, and medicine use that would confound the eventual affiliation with intervention and diabetes danger. Country of start (born in Sweden versus elsewhere) was used as a proxy for broader sociodemographic health-related variations. Home care companies have been included as an indicator of practical dependency. Pre-existing diagnoses, recognized utilizing ICD-10 codes, included myocardial infarction (I21), stroke (I61, I63, I64), angina pectoris (I20), renal illness (N17-N19), power obstructive pulmonary illness (J44), most cancers of the colon and rectum (C18, C20), breast most cancers (C50), psychological and behavioral issues as a result of alcohol use (F10). Medication covariates, recognized utilizing ATC codes, included antihypertensive drugs (C03, C07-C09), lipid-lowering brokers (C10), antidepressants (N06A), and prednisolone (H02AB06). All covariates have been ascertained on or earlier than the index date. No data-driven variable choice procedures have been utilized.
Statistical evaluation
Follow-up time was calculated from the index date (outlined because the second go to inside the HAI program for members and the corresponding assigned date for controls) till the primary prevalence of incident diabetes, demise, or finish of follow-up (December 31, 2022), whichever occurred first. Descriptive statistics have been used to summarize baseline traits.
The unadjusted affiliation between participation within the HAI program and incident diabetes was estimated utilizing Cox proportional hazards regression fashions stratified by matched set to account for particular person matching. The proportional hazards assumption was assessed utilizing Schoenfeld residuals. Adjusted hazard ratios (HRs) and cumulative incidence capabilities have been estimated utilizing Royston–Parmar versatile parametric survival fashions (with splines on the twenty fifth, fiftieth and seventy fifth percentiles of uncensored log survival occasions) with sturdy normal errors clustered by matched set. Royston–Parmar fashions present easy estimates of the underlying survival operate, permitting direct estimation of adjusted cumulative dangers and absolute danger variations. The Royston–Parmar fashions may also accommodate potential violations of the proportional hazards assumption (i.e., time-varying intervention results). Absolute danger estimates and confidence intervals (CIs) have been obtained via refitted bootstrap resampling. Competing-risk sensitivity analyses have been carried out utilizing Fine–Gray subdistribution hazard fashions treating demise as a competing occasion to judge the robustness of the noticed affiliation and to estimate the cumulative incidence of diabetes.
Effect modification was assessed by together with interplay phrases between intervention standing and predefined baseline traits. Population attributable fractions (PAF) have been estimated utilizing model-based predictions to quantify the proportion of incident diabetes statistically attributable to chose baseline danger elements, assuming causal associations.
A normal analysis plan, together with the deliberate analytical method, was agreed upon inside the analysis staff earlier than information evaluation, though it was not formally documented. The analyses reported have been deliberate earlier than information evaluation, and no extra data-driven analyses have been carried out. Statistical analyses and creation of figures have been carried out in R (model 4.5.2; R Foundation for Statistical Computing, Vienna, Austria) in RStudio (model 2025.09.2+418; Posit Software, PBC, Boston, MA, USA).
Ethical approval and information dealing with
The HAI program and the current research have been carried out in accordance with the Declaration of Helsinki and accepted by the Swedish Ethical Review Authority (Number 07-031 with extensions). All members in this system offered written knowledgeable consent to participation within the well being program and to subsequent analysis based mostly on the collected final result information. Individual knowledgeable consent was not obtained for the management inhabitants as they have been recognized via nationwide administrative registers and obtainable to the researchers solely as pseudonymized register information, as accepted by the Swedish Ethical Review Authority. All information dealing with complied with relevant information safety laws.
Generative synthetic intelligence (ChatGPT, GPT-5; OpenAI, San Francisco, CA, USA) was used to help with the event of statistical scripts in R and to enhance readability and language within the textual content. Following the usage of this device, the authors critically reviewed, edited and verified all content material. The authors retain full accountability for the research design, analyses, interpretation of the info, and the ultimate manuscript.
Results
Study inhabitants
The exclusion course of resulted within the exclusion of 626 (9.4%) HAI members and eight,898 (13.4%) controls with prevalent diabetes at baseline. An extra 5 (<0.1%) HAI members and 41 (<0.1%) controls have been excluded as a result of lacking academic information; see Fig 1. The closing research inhabitants comprised 63,561 people, together with 6,018 HAI members and 57,543 matched controls. Mean follow-up was 4.9 years (normal deviation [SD] 2.9) within the HAI cohort and 4.8 years (SD 2.9) within the management cohort, with a complete follow-up time of 29,714 and 276,761 person-years, respectively. During follow-up, incident diabetes occurred in 335 (5.6%) HAI members and three,919 (6.8%) controls. Baseline traits are introduced in Table 1, with extra traits offered in S1 Table.
Primary analyses
Participation within the HAI program was related to a decrease danger of incident diabetes in contrast with controls (adjusted hazard ratio [HR] 0.76; 95% confidence interval [CI] [0.68,0.85]; p < 0.001), additional detailed within the S4 Table. This affiliation was sturdy in unadjusted (S2 and S3 Table) and adjusted sensitivity analyses (S5 Table), together with a mannequin accounting for the competing occasion of demise (S6 Table). The affiliation was constant over time, with no indication of violation of the proportional hazard assumption (p = 0.78). Predicted absolute danger of diabetes, depicted in Fig 2, was 4.85% (95% CI [4.33,5.39]) within the HAI cohort at 5 years and 6.31% (95% CI [6.09,6.55]) amongst controls, equivalent to an absolute danger discount of 1.46 share factors (95% CI [0.91,1.98]; p < 0.001). At 10 years, the corresponding absolute danger distinction was 3.42 share factors (95% CI [2.13,4.75]; p < 0.001). These yielded numbers wanted to deal with of 68 (95% CI [50,110]) and 29 (95% CI [21,46]), respectively. When standardized to the 6,018 HAI members, the model-predicted dangers corresponded to roughly 380 anticipated instances based mostly on the management danger and 292 predicted instances amongst HAI members at 5 years, an estimated distinction of 88 instances (95% CI [55,119]). At 10 years, the corresponding estimates have been 938 and 732 instances, respectively, an estimated distinction of 206 instances (95% CI [128,286]). Detailed cumulative danger analyses outcomes are offered in S7 Table, and figures for noticed danger in S1 Fig.
Fig 2. Predicted cumulative absolute risk of incident diabetes by study group.
Risks were estimated using a multivariable flexible parametric survival model (Royston–Parmar). Shaded areas represent 95% confidence intervals derived from cluster bootstrap resampling of matched sets with model refitting. HAI, Healthy Ageing Initiative.
Secondary analyses
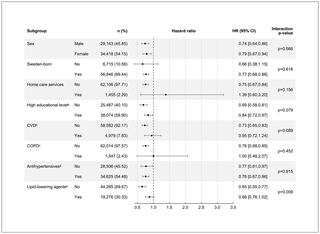
The affiliation between HAI participation and diabetes incidence was broadly constant throughout examined subgroups. There was no statistically important interplay by age, intercourse, nation of start, house care companies, academic degree, CVD, power obstructive pulmonary illness, or use of antihypertensive medicine (Fig 3 and S8 Table). The solely statistically important interplay was noticed to be used of lipid-lowering brokers (p for interplay = 0.008). The affiliation was stronger amongst non-users (HR 0.65; 95% CI [0.55,0.77]) than amongst customers (HR 0.88; 95% CI [0.76,1.02]), for whom the CI included the null. Population attributable fraction (PAF) estimates have been comparable throughout the cohorts and the whole cohort. At 5 years, the estimate was 51.82% (95% CI [51.22,52.42]) within the HAI cohort, 49.05% (95% CI [48.87,49.22]) within the management cohort, and 49.09% (95% CI [48.92,49.26]) within the complete cohort. Detailed PAF estimates are introduced within the S9 Table.
Fig 3. Subgroup-specific associations of participation in the Healthy Ageing Initiative with incident diabetes.
Hazard ratios (HRs) and 95% confidence intervals (CIs) were estimated using separate adjusted Royston–Parmar models with robust standard errors clustered by matched set. HRs compare Healthy Ageing Initiative participants with controls within each subgroup level; values below 1 indicate a lower incidence of diabetes among participants. Squares represent HRs, horizontal lines represent 95% CIs. Interaction p-values were obtained using Wald tests. ICD-10, International Statistical Classification of Diseases and Related Health Problems, 10th Revision. ATC, Anatomical Therapeutic Chemical Classification System. aHigh educational level was defined as >2 years of upper secondary school. bCVD: cardiovascular disease, defined as ICD-10: I21, I61, I63, I64, and/or I20. cCOPD: Chronic obstructive pulmonary disease, ICD-10: J44. dAntihypertensives defined as ATC-codes C03, C07, C08 and C09. eLipid-lowering agents defined as ATC-code C10.
Discussion
In this population-based observational cohort research of older adults, participation in a low-intensity, population-wide preventive well being evaluation program was related to a decrease danger of incident diabetes steady over time, in contrast with matched controls. The affiliation was constant throughout a number of analytical approaches, together with competing-risk analyses, and translated to a probably clinically related absolute danger discount and quantity wanted to deal with over 5 and 10 years. Further, the affiliation with a decrease incidence of diabetes was constant throughout most examined subgroups.
While intensive life-style intervention applications such because the Diabetes Prevention Program and the Finnish Diabetes Prevention Study have demonstrated substantial discount in diabetes incidence in high-risk people [10,12], their depth and managed supply restrict their direct translation to routine care. The current research means that lower-intensity, population-wide approaches may additionally be related to decrease diabetes incidence in routine-care settings. Other European and Nordic initiatives have demonstrated the favorable modifications in life-style elements and cardiometabolic danger profiles, though primarily in additional chosen populations [16–18]. Our findings lengthen these observations by displaying an affiliation with incident diabetes in an older, population-based cohort. Unlike intensive high-risk interventions, the HAI didn’t depend on repeated follow-up or a protocol-driven life-style program, but participation was related to decrease diabetes incidence. These findings recommend that comparatively modest, individually tailor-made preventive efforts delivered at scale might have the potential to contribute to diabetes prevention on the inhabitants degree.
The broadly constant associations throughout the examined subgroups recommend that this system’s potential advantages is probably not confined to particular demographic or scientific teams. This might help not proscribing life-style interventions to teams already at the next cardiometabolic danger. It is vital to notice that a number of the estimates have been imprecise, and the absence of a statistically important interplay shouldn’t be immediately interpreted as proof of similar associations. Although a weaker affiliation was discovered for people utilizing lipid-lowering brokers, these findings must be thought of exploratory. Previous analysis on statins has demonstrated a small elevated danger of diabetes and instructed much less favorable modifications in fasting glucose throughout life-style interventions [27,28]. However, use of lipid-lowering brokers may additionally replicate the next cardiometabolic burden at baseline, and higher preventive efforts inside main care. Because a number of interplay exams have been carried out, these findings must be interpreted cautiously and never as definitive proof that HAI was much less helpful amongst customers of lipid-lowering brokers.
PAF analyses indicated {that a} substantial proportion of incident diabetes instances was related to a handful of chosen baseline danger elements associated to cardiometabolic danger. Although constant in path with earlier population-based analysis [29,30], these outcomes must be interpreted as exploratory because the mannequin assumes causality, and baseline danger elements might act as markers for underlying illness burden relatively than unbiased modifiable targets. Thus, the mechanisms underlying the noticed associations are doubtless multifactorial. The HAI program might improve particular person consciousness of cardiometabolic danger and thereby additional encourage life-style modification related for diabetes prevention. Such results could also be significantly related in older adults, the place adherence to life-style interventions has been proven to be corresponding to, and even larger than, that noticed in youthful populations [7,31].
There are vital strengths of this research. The massive population-based design, with participation from 54% of the eligible inhabitants, and a matched management inhabitants drawn from nationwide inhabitants registers, offers a broad comparability inhabitants and excessive statistical precision. This additionally will increase the real-world side of the outcomes and reveals that the intervention is relevant in a semi-large scale. The use of nationwide registers for follow-up minimized loss to follow-up and ensured final result ascertainment. Using a number of analytical approaches strengthened the robustness of the findings. But a number of limitations also needs to be acknowledged. The observational research design precludes causal inference and can’t exclude residual confounding. Participation within the HAI program was voluntary, elevating the potential of choice bias as a result of a “healthy-volunteer” impact [32]. The HAI cohort had extra favorable values for some baseline traits, and the proportion excluded as a result of prevalent diabetes was decrease than within the management group. Matching and multivariable adjusting can not absolutely compensate for the potential results of such bias. A complete of 209 people initially included as controls subsequently participated within the HAI program and remained within the management cohort within the statistical analyses. This overlap might have launched therapy contamination and attenuated the affiliation in direction of the null if participation diminished their subsequent diabetes danger. The small variety of people concerned means that the potential downward bias might have been restricted, though its magnitude was not quantified. Additionally, information on sure metabolic danger elements akin to plasma glucose ranges and physique mass index, weren’t obtainable for inclusion within the analyses and should have been related for the interpretation of the outcomes. Diabetes diagnoses recorded completely in main care weren’t obtainable within the National Patient Register, and people managed with out glucose-lowering medicine might due to this fact have been recognized later or not captured. Early occasions weren’t excluded to be able to replicate real-world situations.
Taken this under consideration, the findings recommend that preventive applications embedded in routine care and supplied broadly to older adults might characterize a possible complement to intensive high-risk prevention methods for diabetes. Given the alarming incidence of diabetes in getting older populations, even modest danger reductions might translate into substantial absolute advantages at a inhabitants degree. Future analysis ought to intention to judge the cost-effectiveness and implementation methods of program with an analogous total design, in addition to determine which elements contribute most to the noticed associations for simpler future program design. Future research utilizing different approaches might assist make clear the intervention’s position and underlying mechanisms, to tell on optimization in prevention methods for older adults.
In conclusion, participation on this population-wide, low-intensity preventive well being evaluation program aimed toward life-style modification was related to a decrease danger of incident diabetes amongst older adults. However, extra sturdy proof is required to find out the intervention’s contribution to the noticed affiliation, and to raised account for potential healthy-volunteer results. Nevertheless, these findings present real-world help to the potential position of scalable, routine care-based prevention methods in addressing the rising burden of diabetes in getting older populations.
Supporting info
S1 Fig. Cumulative absolute risk of incident diabetes under alternate approaches to death.
The shaded areas represent 95% confidence intervals. A) Estimated using the Kaplan–Meier method, with death treated as censoring. B) Estimated using the Fine-Gray competing risk method, with death treated as a competing event. HAI, Healthy Ageing Initiative.
https://doi.org/10.1371/journal.pmed.1005043.s003
(TIFF)
References
- 1.
GBD 2021 Diabetes Collaborators. Global, regional, and nationwide burden of diabetes from 1990 to 2021, with projections of prevalence to 2050: a scientific evaluation for the Global Burden of Disease Study 2021. Lancet. 2023;402(10397):203–34. pmid:37356446 - 2.
International Diabetes Federation. IDF diabetes Atlas. Brussels: International Diabetes Federation; 2021. Available from: - 3.
World Health Organization. Global report on diabetes. Geneva: World Health Organization; 2016. Available from: - 4.
American Diabetes Association Professional Practice Committee for Diabetes. Older adults: requirements of care in diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S277-96. - 5.
NCD Risk Factor Collaboration (NCD-RisC). Worldwide developments in diabetes prevalence and therapy from 1990 to 2022: a pooled evaluation of 1108 population-representative research with 141 million members. Lancet. 2024;404(10467):2077–93. pmid:39549716 - 6.
Folkhälsomyndigheten. Incidens av diabetes efter ålder i Sverige. Folkhälsomyndigheten. [cited 2026 Jan 3]. Available from: - 7.
Diabetes Prevention Program Research Group. Long-term results of life-style intervention or metformin on diabetes growth and microvascular issues over 15-year follow-up: the Diabetes Prevention Program Outcomes Study. Lancet Diabetes Endocrinol. 2015;3(11):866–75. pmid:26377054 - 8.
Hemmingsen B, Gimenez-Perez G, Mauricio D, Roqué I Figuls M, Metzendorf M-I, Richter B. Diet, bodily exercise or each for prevention or delay of sort 2 diabetes mellitus and its related issues in folks at elevated danger of creating sort 2 diabetes mellitus. Cochrane Database Syst Rev. 2017;12(12):CD003054. pmid:29205264 - 9.
Knowler WC, Barrett-Connor E, Fowler SE, Hamman RF, Lachin JM, Walker EA, et al. Reduction within the incidence of sort 2 diabetes with life-style intervention or metformin. N Engl J Med. 2002;346(6):393–403. pmid:11832527 - 10.
Lindström J, Louheranta A, Mannelin M, Rastas M, Salminen V, Eriksson J, et al. The Finnish Diabetes Prevention Study (DPS): life-style intervention and 3-year outcomes on eating regimen and bodily exercise. Diabetes Care. 2003;26(12):3230–6. pmid:14633807 - 11.
American Diabetes Association Professional Practice Committee for Diabetes. Prevention or delay of diabetes and related comorbidities: requirements of care in diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S50-60. - 12.
Haw JS, Galaviz KI, Straus AN, Kowalski AJ, Magee MJ, Weber MB, et al. Long-term sustainability of diabetes prevention approaches: a scientific evaluation and meta-analysis of randomized scientific trials. JAMA Intern Med. 2017;177(12):1808–17. pmid:29114778 - 13.
Kerrison G, Gillis RB, Jiwani SI, Alzahrani Q, Kok S, Harding SE, et al. The effectiveness of life-style adaptation for the prevention of prediabetes in adults: a scientific evaluation. J Diabetes Res. 2017;2017:8493145. pmid:28567425 - 14.
Aziz Z, Absetz P, Oldroyd J, Pronk NP, Oldenburg B. A scientific evaluation of real-world diabetes prevention applications: learnings from the final 15 years. Implement Sci. 2015;10:172. Epub 20151215. pmid:26670418 - 15.
Andrade CAS, Lovas S, Mahrouseh N, Chamouni G, Shahin B, Mustafa EOA, et al. Primary prevention of sort 2 diabetes mellitus within the European Union: a scientific evaluation of interventional research. Nutrients. 2025;17(6):1053. pmid:40292470 - 16.
Jølle A, Åsvold BO, Holmen J, Carlsen SM, Tuomilehto J, Bjørngaard JH, et al. Basic life-style recommendation to people at excessive danger of sort 2 diabetes: a 2-year population-based diabetes prevention research. The DE-PLAN intervention within the HUNT Study, Norway. BMJ Open Diabetes Res Care. 2018;6(1):e000509. pmid:29765613 - 17.
Manios Y, Lambrinou C-P, Mavrogianni C, Cardon G, Lindström J, Iotova V, et al. Lifestyle modifications noticed amongst adults collaborating in a family- and community-based intervention for diabetes prevention in Europe: the first yr outcomes of the Feel4Diabetes-Study. Nutrients. 2020;12(7):1949. pmid:32629949 - 18.
Norberg M, Wall S, Boman Okay, Weinehall L. The Västerbotten Intervention Programme: background, design and implications. Glob Health Action. 2010;3:10.3402/gha.v3i0.4643. pmid:20339479 - 19.
Galaviz KI, Weber MB, Straus A, Haw JS, Narayan KMV, Ali MK. Global diabetes prevention interventions: a scientific evaluation and community meta-analysis of the real-world impression on incidence, weight, and glucose. Diabetes Care. 2018;41(7):1526–34. pmid:29934481 - 20.
ClinicalTrials.gov. Effects of main prevention on non-communicable illness in aged folks—an intervention research in 70 yr previous women and men, the wholesome getting older initiative [Internet]. Bethesda, MD: National Library of Medicine (US); 2017 [cited 2026 Jan 3]. ClinicalTrials.gov identifier: NCT03312439. Available from: - 21.
Nordström A, Bergman J, Björk S, Carlberg B, Johansson J, Hult A, et al. A a number of danger issue program is related to decreased danger of heart problems in 70-year-olds: a cohort research from Sweden. PLoS Med. 2020;17(6):e1003135. Epub 20200611. pmid:32525878 - 22.
Ludvigsson JF, Andersson E, Ekbom A, Feychting M, Kim J-L, Reuterwall C, et al. External evaluation and validation of the Swedish nationwide inpatient register. BMC Public Health. 2011;11:450. pmid:21658213 - 23.
Brooke HL, Talbäck M, Hörnblad J, Johansson LA, Ludvigsson JF, Druid H, et al. The Swedish reason for demise register. Eur J Epidemiol. 2017;32(9):765–73. pmid:28983736 - 24.
Bröms G, Söderling J, Sachs MC, Halfvarson J, SWIBREG Study Group, Myrelid P, et al. Capturing biologic therapy for IBD within the Swedish Prescribed Drug Register and the Swedish National Patient Register – a validation research. Scand J Gastroenterol. 2021;56(4):410–21. pmid:33632044 - 25.
Johansson J. The Healthy Ageing Initiative: prevention of falls and fractures. Umeå: Umeå University; 2018 [cited 2026 Jan 3]. Available from: - 26.
Statistics Sweden. Individregister och mikrodata [Internet]. Stockholm: Statistics Sweden [cited 2026 Jan 3]. Available from: - 27.
Sattar N, Preiss D, Murray HM, Welsh P, Buckley BM, de Craen AJM, et al. Statins and danger of incident diabetes: a collaborative meta-analysis of randomised statin trials. Lancet. 2010;375(9716):735–42. pmid:20167359 - 28.
Rautio N, Jokelainen J, Oksa H, Saaristo T, Peltonen M, Vanhala M, et al. Do statins intrude with life-style intervention within the prevention of diabetes in main healthcare? One-year follow-up of the FIN-D2D venture. BMJ Open. 2012;2(5):e001472. pmid:22983785 - 29.
Rajaobelina Okay, Dow C, Romana Mancini F, Dartois L, Boutron-Ruault M-C, Balkau B, et al. Population attributable fractions of the principle sort 2 diabetes mellitus danger elements in ladies: findings from the French E3N cohort. J Diabetes. 2019;11(3):242–53. pmid:30098121 - 30.
Naicker Okay, Manuel D, Øverland S, Skogen JC, Johnson JA, Sivertsen B, et al. Population attributable fractions for Type 2 diabetes: an examination of a number of danger elements together with signs of despair and nervousness. Diabetol Metab Syndr. 2018;10:84. pmid:30479670 - 31.
Brokaw SM, Carpenedo D, Campbell P, Butcher MK, Furshong G, Helgerson SD, et al. Effectiveness of an tailored diabetes prevention program life-style intervention in older and youthful adults. J Am Geriatr Soc. 2015;63(6):1067–74. pmid:26031428 - 32.
Lindsted KD, Fraser GE, Steinkohl M, Beeson WL. Healthy volunteer impact in a cohort research: temporal decision within the Adventist Health Study. J Clin Epidemiol. 1996;49(7):783–90. pmid:8691229
This web page was created programmatically, to learn the article in its unique location you may go to the hyperlink bellow:
https://journals.plos.org/plosmedicine/article%3Fid%3D10.1371/journal.pmed.1005043
and if you wish to take away this text from our web site please contact us



