
This web page was created programmatically, to learn the article in its authentic location you’ll be able to go to the hyperlink bellow:
https://journals.plos.org/plosmedicine/article%3Fid%3D10.1371/journal.pmed.1004887
and if you wish to take away this text from our website please contact us
Abstract
Background
Lifestyle interventions are beneficial as first-line therapy in polyendocrine metabolic ovarian syndrome (PMOS), however their effectiveness throughout varied outcomes stays unclear. In this systematic assessment, we consider the effectiveness of way of life interventions on reproductive, anthropometric, and metabolic outcomes.
Methods and findings
We searched Medline, EMBASE, All EBM, PsycInfo, and CINAHL to June 2026 for research analyzing way of life intervention in contrast with minimal or no therapy (standard care) in PMOS. Meta-analyses have been carried out utilizing random-effects mannequin to estimate pooled odd ratios (OR) with 95% confidence intervals (CI). We carried out subgroup analyses to guage variations by intervention sort and period, and by baseline physique mass index (BMI).
A complete of 34 research (1,871 contributors) have been included from the retrieved 1,798 publications. Women who participated in way of life interventions have been extra more likely to obtain common menstrual cycles OR 4.03 (95% CI [1.16, 14.05] I2 = 73%, 5 research, 237 ladies), and have diminished waist circumference imply distinction (MD) −2.38 (95% CI [−4.68, −0.08] I2 = 90%, 18 research, 915 ladies), fasting glucose MD −0.13 (95% CI [−0.25, −0.02] I2 = 86%, 22 research, 1,045 ladies) and fasting insulin MD −6.08 (95% CI [−9.86, −2.30] I2 = 71%, 18 research, 824 ladies) in comparison with ladies who had minimal or no therapy. Subgroup analyses confirmed that weight loss program interventions had larger impact on decreasing fasting glucose ranges whereas train was handiest at decreasing waist circumference and fasting insulin. In ladies with PMOS who have been obese or overweight, way of life interventions led to larger discount in weight, waist/hip ratio, fasting glucose, fasting insulin, complete testosterone, complete ldl cholesterol, and low-density lipoprotein. The predominant limitation of this assessment is the excessive between-study heterogeneity in pooled estimates throughout most of the outcomes.
Conclusion
Our assessment discovered that way of life interventions have been related to improved menstrual regularity and metabolic outcomes in ladies with PMOS, suggesting complementary advantages as no single intervention confirmed general superiority. These findings assist worldwide suggestions, which endorse way of life interventions as first-line therapy, tailor-made to particular person wants.
Author abstract
Why was this research executed?
- Polyendocrine metabolic ovarian syndrome (PMOS) is a typical hormonal situation affecting as much as round 10%–13% of ladies of reproductive age and is linked with irregular menstrual cycle, metabolic issues, and long-term cardiometabolic danger.
- Lifestyle interventions (weight loss program, bodily exercise, behaviour change) are beneficial as first-line therapy in PMOS, however the general effectiveness and the most effective sort and period of those interventions to attain desired reproductive and metabolic outcomes stay unsure.
- An up to date complete synthesis of proof from randomised trials was wanted to tell scientific tips and to make clear which group of ladies profit most from particular way of life interventions.
What did the researchers do and discover?
- We systematically reviewed and meta-analysed randomised managed trials, evaluating way of life interventions with minimal or no interventions. This assessment offers complete subgroup analyses by intervention sort, period and baseline BMI.
- We discovered that general, way of life interventions have been related to elevated odds of attaining common menstrual cycles, and with reductions in central adiposity (waist circumference), fasting glucose, and fasting insulin in contrast with minimal therapy.
- Exercise-based intervention, however not weight loss program or behaviour-only interventions, improved physique mass index, waist circumference, and fasting insulin, whereas dietary and mixed interventions have been notably efficient in reducing fasting glucose.
- In ladies with obese or weight problems, way of life interventions moreover improved weight, waist–hip ratio, complete testosterone, and lipid profile, suggesting cardiometabolic profit on this subgroup.
What do these findings imply?
- These findings assist way of life intervention as a necessary first-line element of PMOS care, reinforcing present worldwide guideline suggestions to prioritise individually tailor-made weight loss program and train assist in symptomatic ladies.
- Different way of life methods could also be extra applicable for various targets, with train notably related for bettering adiposity and insulin resistance, and dietary change extra essential for glycaemic management, particularly in ladies with obese or weight problems.
- Given that many included trials had methodological limitations and heterogeneity in intervention content material and supply, extra rigorous, longer-term research are wanted to outline the simplest and sustainable way of life methods, together with their impression on being pregnant and beginning outcomes.
Citation: Olalere O, Koh M-D, Crabb Ok, Ajijola O, Tariq S, Tay CT, et al. (2026) The impact of way of life interventions in ladies with polyendocrine metabolic ovarian syndrome: A scientific assessment and meta-analysis. PLoS Med 23(9):
e1004887.
https://doi.org/10.1371/journal.pmed.1004887
Academic Editor: Isabelle Dehaene, University Hospital Ghent: Universitair Ziekenhuis Gent, BELGIUM
Received: December 27, 2025; Accepted: August 14, 2026; Published: September 23, 2026
Copyright: © 2026 Olalere et al. This is an open entry article distributed beneath the phrases of the Creative Commons Attribution License, which allows unrestricted use, distribution, and copy in any medium, supplied the unique writer and supply are credited.
Data Availability: All related knowledge are throughout the manuscript and its supporting information information.
Funding: This research was supported by the National Institute for Health and Care Research (NIHR) Birmingham Biomedical Research Centre [https://www.birminghambrc.nihr.ac.uk] (to OO), the Australian National Health and Medical Research Council (NHMRC) fellowships [https://www.nhmrc.gov.au/] (to AM, LM, and HT), and the NIHR Senior Investigator Award [https://www.nihr.ac.uk/career-development/research-career-funding-programmes/professorships-and-senior-investigators/senior-investigators/award] (to ST). The funders had no different function in research design, knowledge assortment and evaluation, determination to publish, or preparation of the manuscript.
Competing pursuits: The authors have declared that no competing pursuits exist.
Abbreviations:
BMI,
physique mass index; CI,
confidence intervals; GRADE,
Grading of Recommendations Assessment, Development and Evaluation; MD,
imply variations; OR,
odd ratios; PCOS,
replaces polycystic ovary syndrome; PMOS,
polyendocrine metabolic ovarian syndrome; PRISMA,
Preferred Reporting Items for Systematic Reviews and Meta-analyses; RCTs,
randomised managed trials; ROB,
Risk of Bias; SD,
customary deviations
Introduction
Polyendocrine metabolic ovarian syndrome (PMOS) is a typical, heterogeneous endocrine-metabolic dysfunction affecting 10% − 13% of ladies of reproductive age [1,2]. This essential, but typically beneath recognised public well being drawback, confers a spread of reproductive, cardiometabolic, dermatologic and psychological sequelae [1]. PMOS accounts for roughly 40% of ladies presenting with subfertility [3], and over 90% of ladies with anovulation attending infertility clinics [4]. Moreover, continual oligo-anovulation leads to extended publicity to unopposed oestrogen, thus growing the danger of endometrial hyperplasia and most cancers. Pregnancy in ladies with PMOS is independently related to elevated maternal and perinatal dangers, that are additional exacerbated by increased physique mass index (BMI) and gestational weight acquire. Consequently, PMOS is taken into account a high-risk being pregnant situation, the place early and sustained way of life modifications could supply potential advantages throughout reproductive well being [5]. An worldwide, multidisciplinary consensus lately adopted the time period polyendocrine metabolic ovarian syndrome (PMOS) to raised mirror the advanced endocrine, metabolic, and reproductive options of the situation. This terminology replaces polycystic ovary syndrome (PCOS) and goals to scale back the stigma and inaccuracies related to the earlier identify [6].
While the precise reason behind PMOS stays unclear, it’s thought to contain a mixture of genetic, environmental and way of life elements [7]. Hallmark options of PMOS embrace hyperinsulinemia, hyperandrogenism and neuroendocrine hormone abnormalities, which contribute to downstream metabolic and reproductive issues. This advanced hormonal milieu contributes to a excessive prevalence of cardiometabolic issues in PMOS, together with weight problems, dyslipidaemia, hypertension, diabetes, gestational diabetes and heart problems [8–10]. Underpinning many of those metabolic and endocrine disturbances is insulin resistance, an intrinsic pathological issue which is exacerbated by obesity-related insulin resistance in PMOS [11,12]. Given its central function, interventions focusing on insulin resistance are key to bettering each scientific and metabolic outcomes in most girls with PMOS [11,13].
Lifestyle interventions, together with train and weight loss program modification, are beneficial as first-line administration for symptomatic ladies with PMOS [1]. These methods are generally used for each weight administration (together with weight reduction, weight upkeep or prevention of extreme weight acquire) and general common cardiometabolic well being enchancment [14]. Recent evaluations [1,15,16] have reported helpful results of way of life interventions on reproductive, metabolic, and anthropometric outcomes in ladies with PMOS. However, current proof is proscribed by the variety of research, variation in intervention varieties, excessive danger of bias, and lack of granularity relating to optimum varieties and durations of interventions [17].
Given the quickly evolving nature of analysis on this discipline, this assessment goals to offer extra complete analysis of the effectiveness of way of life interventions on reproductive, anthropometric, and metabolic outcomes in ladies with PMOS, and to discover whether or not these results differ by intervention sort, period, or baseline physique mass index (BMI).
Methods
We carried out and reported this systematic assessment and meta-analysis in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) tips [18] (S1 Checklist). We prospectively registered the research protocol (PROSPERO CRD42024565919).
Search technique and research choice
We up to date our earlier seek for a 2022 technical report for the International Evidence-based Guideline for the Assessment and Management of PCOS [17] by looking out Ovid Medline, EMBASE, All EBM, PsycInfo, and CINAHL from 1 January 2022 to 9 June 2026, utilizing the identical search phrases (S1 Appendix). There have been no materials variations within the eligibility standards, screening processes, or knowledge synthesis strategies between this assessment and the 2022 technical report. Two reviewers (OO and STq) independently recognized eligible research primarily based on the predefined standards by screening the titles and abstracts after which assessing the total textual content. We resolved disagreements via dialogue and consensus.
We included all randomised managed trials (RCTs) investigating the consequences of way of life interventions on fertility, hormonal, anthropometric and/or metabolic outcomes in ladies with PMOS and utilized no language restrictions. The prognosis of PMOS throughout the included research was in response to NIH 1990, Rotterdam 2003 [19], or AES-PCOS 2006 standards [20]. Eligible way of life interventions included train, weight loss program, behavioural administration or a mixture of those measures for a minimal period of two weeks. We outlined the comparator as minimal therapy which includes no therapy/standard care or customary unstructured minimal dietary, train or behavioural recommendation. Following the CORE outcomes in PCOS [21], we deliberate to evaluate a broad vary of reproductive outcomes (stay beginning, scientific being pregnant, miscarriage, biochemical being pregnant, ovulation, ovarian hyperstimulation, oocyte yield, oocyte maturation fee, period of ovarian stimulation, fertilisation fee, ovarian hyperstimulation syndrome, preterm beginning, gestational age at beginning, gestational diabetes mellitus, pre‑eclampsia, intra‑uterine progress restriction, fetal macrosomia, stillbirth, neonatal demise, perinatal demise, NICU admission, cesarean part and shoulder dystocia). However, within the included trials, extractable reproductive knowledge have been virtually fully restricted to common and irregular menstrual cycles and, in a single research, conception leading to stay beginning. We subsequently handled menstrual cycle regularity as the first reproductive end result and conception/stay beginning as exploratory end result. Other non-reproductive outcomes embrace weight, BMI, waist circumference, waist-hip ratio, intercourse hormone-binding globulin, complete testosterone, free androgen index, fasting glucose, fasting insulin, and lipid profile (complete ldl cholesterol, triglycerides, high-density and low-density lipoprotein ldl cholesterol).
Quality evaluation and knowledge extraction
We used the Cochrane Risk of Bias (ROB) 2.0 software [22] to guage study-level danger of bias throughout 5 domains: randomisation course of, deviations from supposed intervention, incomplete end result knowledge, end result measurement, and selective reporting. Two reviewers independently assessed research high quality, and any disagreements have been resolved via session with a 3rd, unbiased reviewer. We thought of a research as having a low danger of bias if the trial was awarded low danger of bias in all domains, trials with some issues of bias in a single area have been thought of as having a average danger of bias, and trials with a excessive danger of bias in at the least one area or some issues of bias in a number of domains have been thought of as having a excessive danger of bias.
Two reviewers independently extracted knowledge utilizing a pre-designed knowledge extraction sheet. Relevant research traits have been extracted together with yr of publication, nation, participant inclusion and exclusion standards, research intervention, variety of recruited contributors, and particulars of comparator group(s). Dichotomous knowledge have been extracted as 2 × 2 tables, whereas means and customary deviations (SD) have been extracted for steady knowledge. Where medians and interquartile ranges have been reported as an alternative of means and SD, we used medians instead of means and calculated the SD utilizing the system of SD = (third quartile-first quartile)/1.35. Disagreements have been resolved by consensus.
We used Grading of Recommendations Assessment, Development and Evaluation (GRADE) to fee the understanding (excessive, average, low, very low) of proof for all outcomes.
Statistical evaluation
To assess variations between the intervention and management (minimal therapy) teams, we calculated impact sizes for every dichotomous and steady end result, reported as odds ratios (OR) or weighted imply variations (MD), respectively, with corresponding 95% confidence intervals (CI). The research have been weighted primarily based on the inverse of the variance for the evaluated measure with a random-effects mannequin. Heterogeneity was summarised utilizing I2 values, outlined as low, average, or excessive heterogeneity in response to the cut-offs of 25%, 50%, and 75%, respectively. We decided statistical significance utilizing a two-tailed threshold of P < 0.05. All analyses have been carried out on Review Manager model 5 [23].
Sensitivity and subgroup analyses
We carried out sensitivity analyses whereby knowledge from research assessed to have excessive danger of bias have been excluded to gage their impression on the findings. Blinding was not used within the sensitivity evaluation because it was not attainable to blind contributors and the intervention supplier because of the interactive nature of the interventions.
Where knowledge have been accessible, we carried out subgroup analyses to find out the particular proof throughout the following subgroups.
- Component of intervention (dietary alone versus train alone versus behavioural intervention alone versus mixed intervention).
- Duration of intervention (quick: lower than 4 weeks, medium: 4 weeks to a few months, lengthy: larger than three months).
- Studies the place the inclusion criterion was obese contributors versus research with no particular inclusion weight criterion.
We didn’t use any synthetic intelligence software or know-how within the design, screening, knowledge extraction, evaluation, interpretation, or reporting of this research.
Results
Of the 1,798 data retrieved, 34 research (16 retrieved within the present search and 18 from the 2022 technical report) have been included with a complete of 1871 contributors (Fig 1).
Study traits
Seventeen research have been from excessive earnings counties together with Australia [24,25], China [26], Denmark [27], Greece [28], Italy [29–31], the Netherlands [32], Norway [33], Sweden [34,35], UK [36], and USA [37–40], eight have been from two higher center earnings nations Brazil [41–46] and Turkey [47,48], and the remaining 9 research have been carried out in Iran [49–53] and India [54–57] (S2 Appendix).
Using the Cochrane ROB2 software [22], 79% (27/34) of the included research had a low danger of bias for the randomisation course of, 56% (19/34) for impact of task to intervention, 59% (20/34) for impact of adhering to intervention, 79% (27/34) for lacking end result knowledge, 88% (30/34) for meassurement of end result, and 91% (31/34) for collection of reported knowledge. Thirty-five % (12/34) of the included research had an general excessive danger bias (Fig 2, S3 Appendix).
We assessed the standard of the outcomes utilizing the GRADE rating system (S4 Appendix).
Effect of way of life interventions on reproductive outcomes
Women with PMOS who had way of life interventions had elevated odds of attaining common menstrual cycles OR 4.03 (95% CI [1.16, 14.05] I2 = 73%, 5 research, 237 ladies) than ladies who had minimal therapy.
Only one of many included research [58] reported on conception leading to stay beginning. This follow-up research on being pregnant outcomes from a RCT assessing way of life interventions (a mixture of normo-caloric weight loss program, train in response to the World Health Organization’s Global Recommendations, and cognitive behavioural remedy) in obese/overweight ladies with PMOS discovered that 39.8% (49/123) of these within the intervention group achieved being pregnant which resulted in stay beginning, in comparison with 38.3% (23/60) of ladies within the standard care group [58]. The discovering was not statistically important.
No different deliberate fertility or being pregnant outcomes had ample or constant reporting to permit quantitative synthesis.
Effect of way of life interventions on anthropometric and metabolic outcomes
Compared to ladies with PMOS who had minimal therapy, those that had way of life interventions exhibited larger reductions in waist circumference MD −2.38 (95% CI [−4.68, −0.08] I2 = 90%, 18 research, 915 ladies), fasting glucose MD −0.13 (95% CI [−0.25, −0.02] I2 = 86%, 22 research, 1,045 ladies), and fasting insulin MD −6.08 (95% CI [−9.86, −2.30] I2 = 71%, 18 research, 824 ladies). There have been no important variations between teams when evaluating results on weight, BMI, waist circumference, waist-hip ratio, intercourse hormone binding globulin, complete testosterone, free androgen index, or lipid profile (Table 1).
Sensitivity analyses
Following the exclusion of research with an general excessive danger of bias ranking, solely the helpful impact of way of life interventions on fasting insulin MD −5.71 pmol/L (95percentCI [−9.60, −1.83] P = 0.004) in contrast with minimal therapy endured, whereas variations in fasting glucose and waist circumference have been attenuated MD −0.07 (95% CI [−0.20, 0.06]) and MD −1.94 (95% CI [−3.93, 0.05]), respectively (Table 2).
However, the impact of way of life interventions on androgen markers and lipid profiles remained inconclusive.
Subgroup analyses
Intervention sort subgroups.
There was proof of subgroup variations by varieties of intervention for BMI, waist circumference, fasting glucose, fasting insulin, and low-density lipoproteins (Table 3).
Exercise-based interventions show larger discount in post-intervention BMI MD −0.81 kg/m2 (95% CI [−1.60, −0.02] P = 0.04; Fig 3a), waist circumference MD −3.17 cm (95% CI –[5.61, −0.73] P = 0.01; Fig 3b), fasting insulin MD −1.86 pmol/L (95% CI [−2.96, −0.76] P = 0.0009; Fig 3c) in contrast with minimal therapy.
There have been no important variations in BMI in those that had weight loss program modification MD 0.43 kg/m2 (95% CI [−1.42, 2.28] P = 0.65), behaviour change MD −0.44 kg/m2 (95% CI [−1.68, 0.08] P = 0.49), or a mixed intervention MD 0.95 kg/m2 (95% CI [−4.09, 5.98] P = 0.71) versus those that had minimal therapy (Fig 3a). No variations in waist circumference have been seen between ladies who had weight loss program modification or mixed interventions versus those that had minimal therapy, with a MD −1.77 cm (95% CI [−8.82, 5.28] P = 0.62) and MD 4.6 cm (95% CI [−12.03, 21.23] P = 0.59) (Fig 3b). Diet, behaviour change, or mixed interventions didn’t present important distinction on fasting insulin compared with minimal therapy (Fig 3c).
There have been no important variations in weight amongst ladies who had train, weight loss program modification, behaviour change, or mixed interventions versus those that had minimal therapy, with MD −2.33 kg, (95% CI [−5.42, 0.75] P = 0.14), −0.84 kg (95% CI [−4.10, 2.43] P = 0.61), −0.74 kg (95% CI [−2.43, 0.95] p = 0.39), and 1 kg (95% CI [−17.1, 19.1] p = 0.91), respectively (Fig 3d).
Diet modifications and mixed interventions had important discount on fasting glucose ranges in comparison with minimal therapy with MDs of −0.38 mmol/L (95% CI [−0.60, −0.17] P = 0.0005) and −0.42 mmol/L (95% CI [−0.44, −0.40] P < 0.00001), respectively. There have been no variations in fasting glucose in ladies who had train or behaviour change interventions versus minimal therapy, with MDs of −0.01 mmol/L (95% CI [−0.18, 0.16] P = 0.92) and −0.22 mmol/L (95% CI [−0.45, 0.01] P = 0.06), respectively (Fig 3e).
Combined interventions show larger discount in post-intervention low-density lipoproteins MD −0.66 mmol/L (95% CI [−1.25, −0.08] p = 0.03). However, no distinction was seen within the stage of low-density lipoprotein between ladies who train, weight loss program or behaviour remedy alone in comparison with those that had minimal therapy (Table 3).
There have been no statistically important variations primarily based on the kind of way of life intervention for all different measured outcomes together with waist-hip ratio, intercourse hormone-binding globulin, complete testosterone, free androgen index, complete ldl cholesterol, high-density lipoprotein, and triglycerides (Table 3, S5 Appendix).
Intervention period subgroups.
There have been general subgroup variations by period of intervention for waist circumference, fasting glucose or fasting insulin (all P < 0.05). Within subgroups, way of life interventions lasting for one to a few months had larger reductions in, fasting glucose and fasting insulin in comparison with minimal therapy MD −0.25 mmol/L (95% CI [−0.43, −0.07] p < 0.01) and MD −7.03 pmol/L (95% CI [−12.47, −1.59] p < 0.01), respectively (Table 4). Interventions lasting greater than three months have been efficient in decreasing complete testosterone ranges MD −0.18nmol/L (95% CI [−0.36, −0.01] p = 0.04). There have been no important variations by period of way of life intervention for all different measured outcomes (Table 4, S5 Appendix).
Baseline BMI standing subgroups.
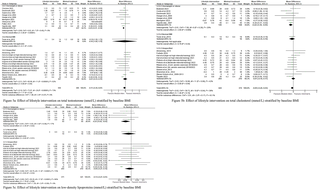
Lifestyle interventions within the obese or overweight subgroup demonstrated larger reductions in weight MD −2.19 kg (95% CI [−3.35, −1.02] p = 0.004, Fig 4a), waist-hip ratio MD −0.03 (95% CI [−0.06, −0.01] p = 0.007, Fig 4b), fasting glucose MD −0.22 mmol/L (95% CI [−0.36, −0.07] p = 0.004, Fig 4c), fasting insulin MD −12.98 pmol/L (95% CI [−23.22, −2.74] p = 0.01, Fig 4d), complete testosterone MD −0.25 nmol/L (95% CI [−0.37, −0.14] p < 0.00001, Fig 5a), complete ldl cholesterol MD −0.22 mmol/L (95% CI [−0.38, −0.05] p = 0.09, Fig 5b), and low-density lipoproteins MD −0.23 mmol/L (95% CI [−0.42, −0.03] p = 0.02, Fig 5c) in contrast with minimal therapy. Within subgroups with regular or unspecified baseline BMI, there have been no variations in any outcomes between way of life interventions and minimal therapy (Table 5, S2 Appendix).
There have been no important subgroup variations by baseline BMI standing (obese or overweight versus regular versus unspecified BMI) for any of the opposite outcomes assessed (Table 5, S5 Appendix).
Discussion
This systematic assessment and meta-analysis present quantitative estimates of the consequences of way of life interventions on reproductive, anthropometric and metabolic outcomes in ladies with PMOS. Overall, way of life intervention led to greater than 4-fold enhance within the odds of attaining common menstrual cycles. Significant reductions in waist circumference, fasting glucose and fasting insulin have been additionally noticed compared with minimal therapy. Subgroup analyses revealed variation in impact by intervention sort, period, and baseline BMI standing, with helpful results on different outcomes seen inside sure subgroups. Exercise-based interventions improved anthropometric outcomes and fasting insulin in contrast with minimal therapy. Similarly, way of life interventions lasting one to a few months led to important reductions in fasting glucose and fasting insulin, whereas interventions lasting greater than three months improved complete testosterone stage. Among the subgroup of contributors with baseline obese or weight problems, way of life intervention improved weight, waist-hip ratio, complete testosterone, and lipid profile in contrast with minimal therapy.
The predominant power of this assessment is the strong methodology, incorporation of the latest proof so far and constructing on prior systematic evaluations. With the inclusion of 34 research, making it essentially the most complete evaluation so far on the impression of weight loss program, train, and behavior adjustments on a spread of outcomes in PMOS. This assessment expands on present information and improves generalisability of the findings by together with research from high-, upper-middle-, and lower-middle-income nations.
The predominant limitation of this assessment was that over a 3rd of the included research had general excessive danger of bias, reflecting methodological weaknesses which can result in misrepresentation of the true results of way of life interventions. To mitigate this, we carried out sensitivity evaluation by excluding these research to determine their affect on the findings. Another limitation is the broad definition of way of life interventions, which embody all kinds of weight loss program, train, behavioural, or mixed interventions and contribute to heterogeneity in our findings. In addition, we included research that used totally different PMOS diagnostic standards (NIH 1990, Rotterdam 2003, and AES‑PCOS 2006), which can have resulted in variation in baseline phenotype and end result responses throughout trials and characterize an extra essential supply of scientific heterogeneity. Due to substantial statistical heterogeneity throughout most outcomes, we didn’t formally assess publication bias utilizing funnel plots or Egger’s check as they could be tough to interpret in these situations. Participant traits and baseline danger profiles may differ and have an effect on intervention responses. We addressed this to some extent with the inclusion of subgroup analyses by sort and period of way of life intervention and by baseline BMI classes of research contributors. However, whereas these sub-analyses can present worthwhile insights into the differential results attributable to these elements, statistical energy is proscribed, notably for some subgroups with small numbers of research. Lastly, though most of the included research adjusted for confounders, the variability in intervention protocols and end result measurements throughout the included research could have launched further confounders similar to cultural dietary patterns and variations in adherence to interventions that are tough to standardise throughout research and areas. In addition, a proper evaluation of research integrity was not undertaken as a result of this assessment focussed on trial-level danger of bias and proof certainty utilizing the Cochrane RoB 2 software and GRADE.
Improving on a earlier assessment [1] which recognized solely two research reporting on reproductive outcomes, we included 5 research reporting on the consequences of way of life interventions on menstrual regularity; three research assessed menstrual regularity on the finish of the research with out specifying the precise time to cycle normalisation, one research reported common menses at 90–120 days, and one research assessed this end result by 6 months. Overall, we discovered way of life interventions to be related to an over 4-fold enhance within the odds of attaining common cycles. Of the 5 research offering knowledge for this evaluation, three [24,30,47] included contributors with baseline obese or weight problems whereas the baseline BMI of the contributors within the remaining two [26,56] have been unspecified. This discovering aligns with that of one other systematic assessment of two research involving ladies with PMOS and weight problems, which discovered equally improved menstrual cycles with way of life intervention OR 4.34 (95% CI [1.75, 10.78] p = 0.02) [59]. This substantial enchancment in ovulatory perform affords ladies with PMOS a compelling non-pharmacological first-line choice, notably reassuring given widespread fertility issues. Unlike pharmacological therapies (mixed oral contraceptives, insulin sensitizers, anti-androgens) carrying hostile impact dangers, way of life interventions demonstrated reproductive advantages with out drugs, with three of 5 research particularly together with obese/overweight contributors the place PMOS cardiometabolic danger is highest [59].
Previous evaluations have reported totally different results of way of life intervention on weight reduction in ladies with PMOS, probably as a consequence of variations within the inclusion standards, intervention varieties and period within the included research. The 2019 Cochrane assessment involving 9 research and 353 ladies urged that there was low-quality proof that way of life intervention results in higher weight reduction in comparison with minimal therapy MD −1.68 kg (95% CI [−2.66, −0.70]) [14]. This discovering aligns with one other systematic assessment that additionally reported helpful results of way of life interventions on weight administration in ladies with PMOS and weight problems, though that assessment was primarily based on solely three research [59]. More latest syntheses, together with a 2025 assessment of randomised managed trials revealed within the final 10 years [60] and one other assessment of observational and interventional research recognized in 2022 [16] have additionally typically supported modest enhancements in weight. Our assessment didn’t discover a statistically important general impact of way of life interventions on weight in comparison with minimal therapy which is in step with findings of our earlier assessment MD −1.02 (95% CI [−2.08, 0.04] p = 0.058) [17].
Importantly, subgroup evaluation restricted to ladies with obese or weight problems discovered a major discount in weight with way of life interventions, suggesting that the consequences are extra pronounced on this inhabitants. These findings spotlight the necessity to take into account the impression of participant traits, research design, intervention sort and period when decoding accessible proof. Exercise, notably moderate-to-vigorous cardio train and mixed aerobic-resistance coaching, most successfully reduces waist circumference and visceral adipose tissue in obese and overweight adults, producing clinically significant enhancements in metabolic outcomes together with insulin sensitivity, glycaemic management, lipid profiles, and general cardiometabolic danger. These reductions happen, partly, via preferential lipolysis and oxidation of visceral fats, pushed by its heightened responsiveness to exercise-induced catecholamines and myokines (similar to IL-6) relative to subcutaneous depots. Higher-intensity protocols typically amplify this impact in a dose-dependent method [61].
The earlier assessment reported that way of life interventions improved waist circumference MD −1.32 cm (95% CI [−2.46, −0.18] 12 research), waist/hip ratio MD −0.03 (95% CI [−0.05, −0.01] 6 research), complete ldl cholesterol MD −0.15 mmol/L (95% CI [−0.26, −0.03] 12 research) and low density lipoprotein ldl cholesterol MD −0.15 mmol/L (95% CI [−0.28, −0.02] 12 research) in comparison with minimal therapy in ladies with PMOS [1]. In this assessment, the numerous helpful results of way of life interventions on waist circumference have been corroborated in a bigger evaluation involving pooled knowledge from 17 research. However, the numerous results on waist/hip ratio complete ldl cholesterol and low-density lipoprotein ldl cholesterol have been solely noticed among the many subgroup of ladies with baseline obese or weight problems in subgroup evaluation. Reductions in waist circumference, fasting glucose and fasting insulin translate to clinically significant enhancements in central adiposity and insulin resistance, key drivers of PMOS cardiometabolic danger.
While the 2019 Cochrane assessment discovered that way of life interventions could enhance free androgen index (MD −1.11 (95% CI [−1.96, −0.26] 6 research, 204 ladies, I2 = 71%, low-quality proof)) [14], we discovered no important general impact on free androgen index or complete testosterone. However, subgroup analyses show larger reductions in complete testosterone (MD −0.25 nmol/L (95% CI [−0.37, −0.14] 9 research, 475 ladies)) particularly amongst ladies with baseline obese or weight problems, indicating specific profit for this inhabitants. Similarly, whereas the Cochrane assessment discovered way of life interventions to be efficient in decreasing complete ldl cholesterol (MD −0.14 mmol (95% CI [−0.25, −0.02] 9 research, 331 ladies)) and low-density lipoprotein ranges (MD −0.16 mmol (95% CI [−0.29, −0.03] 9 research, 326 ladies)) [14], we discovered statistically important helpful results solely within the subgroup of contributors with baseline obese or weight problems.
In our pooled evaluation of 18 research, way of life intervention considerably diminished fasting insulin ranges. This discovering aligns with, and broaden on that of the sooner evaluations that included 14 and 10 research, which additionally reported important reductions in fasting insulin MD of −1.8 pmol/L (95% CI [−3.10, −0.65]) [1] and MD −1.42 µU/mL (95% CI [−2.44, −0.39]) [14], respectively. In each the sooner assessment [1] and the 2019 Cochrane assessment [14], there have been no variations in fasting glucose ranges between the approach to life intervention and minimal therapy teams in pooled analyses of 15 and 11 research, respectively. With 22 included research, we discovered that way of life intervention led to important reductions in fasting glucose ranges; nonetheless, this was not corroborated in a sensitivity evaluation the place research with excessive danger of bias have been excluded, suggesting warning in interpretation of this discovering.
The findings of this assessment reinforce the significance of way of life interventions as a first-line strategy for managing symptomatic ladies with PMOS. The noticed enhancements in menstrual regularity, central adiposity, fasting glucose and fasting insulin ranges related to way of life interventions spotlight the potential advantages of incorporating these approaches as important parts of scientific PMOS care. These outcomes assist the 2023 International Evidence-based Guideline for the Assessment and Management of PCOS, which recommends way of life intervention because the preliminary step in administration [1]. Clinicians ought to prioritise exercise-based packages for bettering central adiposity and insulin resistance, and dietary interventions for glycaemic management, notably in these with obese or weight problems the place cardiometabolic advantages are most pronounced. Implementation requires multidisciplinary assist (e.g., dietitians, physiotherapists) and digital instruments for adherence, with shared decision-making to tailor methods to affected person preferences and boundaries.
Our analyses point out that totally different way of life interventions could also be more practical for particular outcomes or inhabitants subgroups, underscoring the significance of personalised care. Diet modifications—encompassing a heterogeneous vary of dietary approaches are urged to be extra applicable in managing glucose ranges, whereas train interventions, alongside which sufferers typically adopted modest dietary restriction could also be higher fitted to bettering BMI and waist circumference and decreasing insulin ranges. Additionally, amongst PMOS subgroups with obese and weight problems, way of life interventions improved weight, fasting glucose, insulin, testosterone, and dyslipidaemia, suggesting specific profit on this subgroup for managing cardiometabolic danger.
Taken collectively, these findings emphasise the necessity for future analysis into the mechanisms via which particular way of life methods impression reproductive, anthropometric, and metabolic parameters in PMOS. Notably, 78% of the included research on this assessment have been assessed as having some issues or excessive danger of bias. This underscores the necessity for better-designed and applied trials, prioritise methodological rigour, together with applicable randomisation, blinding of therapy allocation, and standardised end result reporting. Additional analysis can also be wanted to determine the consequences of way of life interventions throughout the Rotterdam PCOS phenotypes (A: hyperandrogenism + ovulatory dysfunction + polycystic ovarian morphology; B: hyperandrogenism + ovulatory dysfunction; C: hyperandrogenism + polycystic ovarian morphology; D: ovulatory dysfunction + polycystic ovarian morphology), as responses could differ relying on underlying pathophysiology [19,62,63]. A extra nuanced understanding of those variations can assist the event of tailor-made and evidence-based approaches to care. Lifestyle interventions considerably improved menstrual regularity and diminished waist circumference, fasting glucose and insulin ranges in comparison with minimal therapy, reinforcing their function as a first-line strategy in PMOS administration. These findings emphasise the significance of personalised care, with tailor-made way of life interventions to handle the various wants of ladies with PMOS. Further analysis is required to establish the simplest intervention parts and combos for particular outcomes, and their impacts on fertility and broader outcomes together with psychological options in PMOS.
Acknowledgments
We thank the authors of the first research included on this assessment for making their analysis accessible and for his or her dedication to analysis.
References
- 1.
Teede H, Tay CT, Laven J. et al. International evidence-based guideline for the evaluation and administration of polycystic ovary syndrome. Monash University; 2023. - 2.
Parker J, O’Brien C, Hawrelak J, Gersh FL. Polycystic ovary syndrome: an evolutionary adaptation to way of life and the atmosphere. Int J Environ Res Public Health. 2022;19(3):1336. pmid:35162359 - 3.
Teede H, Deeks A, Moran L. Polycystic ovary syndrome: a posh situation with psychological, reproductive and metabolic manifestations that impacts on well being throughout the lifespan. BMC Med. 2010;8:41. pmid:20591140 - 4.
Sirmans S, Pate Ok. Epidemiology, prognosis, and administration of polycystic ovary syndrome. Clin Epidemiol 2013:1. - 5.
Bahri Khomami M, Hashemi S, Shorakae S, Harrison CL, Piltonen TT, Romualdi D, et al. Systematic assessment and meta-analysis of beginning outcomes in ladies with polycystic ovary syndrome. Nat Commun. 2024;15(1):5592. pmid:38965241 - 6.
Teede HJ, Khomami MB, Morman R, Laven JSE, Joham AE, Costello MF, et al. Polyendocrine metabolic ovarian syndrome, the brand new identify for polycystic ovary syndrome: a multistep international consensus course of. Lancet. 2026;407(10545):2329–39. pmid:42119588 - 7.
Mykhalchenko Ok, Lizneva D, Trofimova T, Walker W, Suturina L, Diamond MP, et al. Genetics of polycystic ovary syndrome. Expert Rev Mol Diagn. 2017;17(7):723–33. pmid:28602111 - 8.
Apridonidze T, Essah PA, Iuorno MJ, Nestler JE. Prevalence and traits of the metabolic syndrome in ladies with polycystic ovary syndrome. J Clin Endocrinol Metab. 2005;90(4):1929–35. pmid:15623819 - 9.
Chen W, Pang Y. Metabolic Syndrome and PCOS: pathogenesis and the function of metabolites. Metabolites. 2021;11(12):869. pmid:34940628 - 10.
Tay CT, Mousa A, Vyas A, Pattuwage L, Tehrani FR, Teede H. 2023 worldwide evidence-based polycystic ovary syndrome guideline replace: insights from a scientific assessment and meta-analysis on elevated scientific heart problems in polycystic ovary syndrome. J Am Heart Assoc. 2024;13(16):e033572. pmid:39119982 - 11.
Teede HJ, Hutchison SK, Zoungas S. The administration of insulin resistance in polycystic ovary syndrome. Trends Endocrinol Metab. 2007;18(7):273–9. pmid:17698366 - 12.
Diamanti-Kandarakis E, Papavassiliou AG. Molecular mechanisms of insulin resistance in polycystic ovary syndrome. Trends Mol Med. 2006;12(7):324–32. pmid:16769248 - 13.
Stepto NK, Cassar S, Joham AE, Hutchison SK, Harrison CL, Goldstein RF, et al. Women with polycystic ovary syndrome have intrinsic insulin resistance on euglycaemic-hyperinsulaemic clamp. Hum Reprod. 2013;28(3):777–84. pmid:23315061 - 14.
Lim SS, Hutchison SK, Van Ryswyk E, Norman RJ, Teede HJ, Moran LJ. Lifestyle adjustments in ladies with polycystic ovary syndrome. Cochrane Database Syst Rev. 2019;3(3):CD007506. pmid:30921477 - 15.
Long JR, Parker M, Jumani S, Ahmed A, Huynh V, Gomez-Lobo V. Effect of way of life modifications on polycystic ovary syndrome in predominantly younger adults: a scientific assessment. J Pediatr Adolesc Gynecol. 2025;38(2):139-147.e4. pmid:39577757 - 16.
Mohamed AH, Albasheer O, Ghoniem MA, Abdalghani N, Ayish F, Abdelwahab SI, et al. Impact of way of life interventions on reproductive and psychological outcomes in ladies with polycystic ovary syndrome: a scientific assessment. Medicine (Baltimore). 2025;104(3):e41178. pmid:39833063 - 17.
Mousa A, Tay CT, Teede H. Technical report for the 2023 worldwide evidence-based guideline for the evaluation and administration of polycystic ovary syndrome. Monash University; 2023. - 18.
Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD, et al. The PRISMA 2020 assertion: an up to date guideline for reporting systematic evaluations. Rev Esp Cardiol (Engl Ed). 2021;74(9):790–9. pmid:34446261 - 19.
Rotterdam ESHRE/ASRM-Sponsored PCOS Consensus Workshop Group. Revised 2003 consensus on diagnostic standards and long-term well being dangers associated to polycystic ovary syndrome. Fertil Steril. 2004;81(1):19–25. pmid:14711538 - 20.
Azziz R, Carmina E, Dewailly D, Diamanti-Kandarakis E, Escobar-Morreale HF, Futterweit W, et al. Positions assertion: standards for outlining polycystic ovary syndrome as a predominantly hyperandrogenic syndrome: an Androgen Excess Society guideline. J Clin Endocrinol Metab. 2006;91(11):4237–45. pmid:16940456 - 21.
Al Wattar BH, Teede H, Garad R, Franks S, Balen A, Bhide P, et al. Harmonising analysis outcomes for polycystic ovary syndrome: a global multi-stakeholder core end result set. Hum Reprod. 2020;35(2):404–12. pmid:32020203 - 22.
Sterne JAC, Savović J, Page MJ, Elbers RG, Blencowe NS, Boutron I, et al. RoB 2: a revised software for assessing danger of bias in randomised trials. BMJ. 2019;:l4898. - 23.
Review Manager (RevMan) [Internet]. Version 5. The Cochrane Collaboration; 2024 [cited 2024 Sep 8]. Available from: - 24.
Patten RK, McIlvenna LC, Levinger I, Garnham AP, Shorakae S, Parker AG, et al. High-intensity coaching elicits larger enhancements in cardio-metabolic and reproductive outcomes than moderate-intensity coaching in ladies with polycystic ovary syndrome: a randomized scientific trial. Hum Reprod. 2022;37(5):1018–29. pmid:35325125 - 25.
Kiel IA, Lionett S, Parr EB, Jones H, Røset MAH, Salvesen Ø. 1 High-intensity interval coaching in polycystic ovary syndrome: a two-centre, three-armed 2 randomized managed trial. n.d. - 26.
Mei S, Ding J, Wang Ok, Ni Z, Yu J. Mediterranean weight loss program mixed with a low-carbohydrate dietary sample within the therapy of obese polycystic ovary syndrome sufferers. Front Nutr. 2022;9:876620. pmid:35445067 - 27.
Moeller LV, Lindhardt CL, Andersen MS, Glintborg D, Ravn P. Motivational interviewing in overweight ladies with polycystic ovary syndrome – a pilot research. Gynecol Endocrinol. 2019;35(1):76–80. pmid:30182773 - 28.
Stefanaki C, Bacopoulou F, Livadas S, Kandaraki A, Karachalios A, Chrousos GP, et al. Impact of a mindfulness stress administration program on stress, nervousness, melancholy and high quality of life in ladies with polycystic ovary syndrome: a randomized managed trial. Stress. 2015;18(1):57–66. pmid:25287137 - 29.
Vigorito C, Giallauria F, Palomba S, Cascella T, Manguso F, Lucci R, et al. Beneficial results of a three-month structured train coaching program on cardiopulmonary useful capability in younger ladies with polycystic ovary syndrome. J Clin Endocrinol Metab. 2007;92(4):1379–84. pmid:17264174 - 30.
Meneghini C, Bianco C, Galanti F, Tamburelli V, Dal Lago A, Licata E, et al. The impression of dietary remedy within the administration of obese/overweight PCOS affected person candidates for IVF. Nutrients. 2023;15(20):4444. pmid:37892519 - 31.
Cincione IR, Graziadio C, Marino F, Vetrani C, Losavio F, Savastano S, et al. Short-time results of ketogenic weight loss program or modestly hypocaloric Mediterranean weight loss program on obese and overweight ladies with polycystic ovary syndrome. J Endocrinol Invest. 2023;46(4):769–77. pmid:36401759 - 32.
Dietz de Loos A, Jiskoot G, Beerthuizen A, Busschbach J, Laven J. Metabolic well being throughout a randomized managed way of life intervention in ladies with PCOS. Eur J Endocrinol. 2021;186(1):53–64. pmid:34714771 - 33.
Almenning I, Rieber-Mohn A, Lundgren KM, Shetelig Løvvik T, Garnæs KK, Moholdt T. Effects of excessive depth interval coaching and power coaching on metabolic, cardiovascular and hormonal outcomes in ladies with polycystic ovary syndrome: a pilot research. PLoS One. 2015;10(9):e0138793. pmid:26406234 - 34.
Stener-Victorin E, Holm G, Janson PO, Gustafson D, Waern M. Acupuncture and bodily train for affective signs and health-related high quality of life in polycystic ovary syndrome: secondary evaluation from a randomized managed trial. BMC Complement Altern Med. 2013;13:131. pmid:23763822 - 35.
Oberg E, Gidlöf S, Jakson I, Mitsell M, Tollet Egnell P, Hirschberg AL. Improved menstrual perform in overweight ladies with polycystic ovary syndrome after behavioural modification intervention: a randomized managed trial. Clin Endocrinol (Oxf). 2019;90(3):468–78. pmid:30565716 - 36.
Deshmukh H, Papageorgiou M, Wells L, Akbar S, Strudwick T, Deshmukh Ok, et al. The impact of a Very-Low-Calorie Diet (VLCD) vs. a average vitality deficit weight loss program in overweight ladies with Polycystic Ovary Syndrome (PCOS): a randomised managed trial. Nutrients. 2023;15(18):3872. pmid:37764656 - 37.
Brown AJ, Setji TL, Sanders LL, Lowry KP, Otvos JD, Kraus WE, et al. Effects of train on lipoprotein particles in ladies with polycystic ovary syndrome. Med Sci Sports Exerc. 2009;41(3):497–504. pmid:19204602 - 38.
Guzick DS, Wing R, Smith D, Berga SL, Winters SJ. Endocrine penalties of weight reduction in overweight, hyperandrogenic, anovulatory ladies. Fertil Steril. 1994;61(4):598–604. pmid:8150098 - 39.
Hoeger KM, Kochman L, Wixom N, Craig Ok, Miller RK, Guzick DS. A randomized, 48-week, placebo-controlled trial of intensive way of life modification and/or metformin remedy in obese ladies with polycystic ovary syndrome: a pilot research. Fertil Steril. 2004;82(2):421–9. pmid:15302293 - 40.
Hoeger Ok, Davidson Ok, Kochman L, Cherry T, Kopin L, Guzick DS. The impression of metformin, oral contraceptives, and way of life modification on polycystic ovary syndrome in overweight adolescent ladies in two randomized, placebo-controlled scientific trials. J Clin Endocrinol Metab. 2008;93(11):4299–306. pmid:18728175 - 41.
Costa EC, DE Sá JCF, Stepto NK, Costa IBB, Farias-Junior LF, Moreira SDNT, et al. Aerobic coaching improves high quality of life in ladies with polycystic ovary syndrome. Med Sci Sports Exerc. 2018;50(7):1357–66. pmid:29443823 - 42.
Kogure GS, Lopes IP, Ribeiro VB, Mendes MC, Kodato S, Furtado CLM, et al. The results of cardio bodily workouts on physique picture amongst ladies with polycystic ovary syndrome. J Affect Disord. 2020;262:350–8. pmid:31735408 - 43.
Ribeiro VB, Lopes IP, Dos Reis RM, Silva RC, Mendes MC, Melo AS, et al. Continuous versus intermittent cardio train within the enchancment of high quality of life for ladies with polycystic ovary syndrome: a randomized managed trial. J Health Psychol. 2021;26(9):1307–17. pmid:31495231 - 44.
Miranda Furtado CL, Hansen M, Kogure GS, Ribeiro VB, Taylor N, Racy Soares M, et al. Resistance and cardio coaching will increase genome-wide DNA methylation in ladies with polycystic ovary syndrome. Epigenetics. 2024;19(1):2305082. pmid:38245873 - 45.
Philbois SV, Ribeiro VB, Tank J, Dos Reis RM, Gerlach DA, Souza HCD. Cardiovascular autonomic modulation variations between moderate-intensity steady and high-intensity interval cardio coaching in ladies with PCOS: a randomized trial. Front Endocrinol (Lausanne). 2022;13:1024844. pmid:36568110 - 46.
Colonetti L, Uggioni MLR, Prestes G da S, Stangherlin L, Junior JCD, Moura R, et al. Effects of carbohydrate diminished weight loss program related to power coaching on scientific indicators of ladies with polycystic ovary syndrome: randomized scientific trial. Nutrition. 2025;133:112696. pmid:40048764 - 47.
Bozbulut R, Döğer E, Çamurdan MO, Bideci A. Beneficial results of RESMENA weight loss program on anthropometric, metabolic, and reproductive profile in adolescents with weight problems and polycystic ovary syndrome: a randomized managed intervention research. Horm Res Paediatr. 2024;97(5):483–95. pmid:37952514 - 48.
Turan V, Mutlu EK, Solmaz U, Ekin A, Tosun O, Tosun G, et al. Benefits of short-term structured train in non-overweight ladies with polycystic ovary syndrome: a potential randomized managed research. J Phys Ther Sci. 2015;27(7):2293–7. pmid:26311969 - 49.
Nasrekani Z, Fathi M. The impact of 12 weeks cardio coaching on physique composition, cardio energy and a few hormones in infertile ladies with polycystic ovary syndrome. Iran J Obstet Gynecol Infertil. 2016;19(5):1–10. (Persian). - 50.
Saremi A, Shoundi N, Kermani M, Kazemi M. Serum anti-Müllerian hormone ranges after train coaching in ladies with polycystic ovary syndrome: a randomized scientific trial. Iran J Obstet Gynecol Infertil. 2013;16(64):10–8. (Persian). - 51.
Nikrad N, Farhangi MA, Fard Tabrizi FP, Vaezi M, Mahmoudpour A, Mesgari-Abbasi M. The impact of calorie-restriction together with thylakoid membranes of spinach on the gut-brain Axis Pathway and oxidative stress biomarkers in overweight ladies with polycystic ovary syndrome: a Randomized, Double-blind, placebo-controlled scientific trial. J Ovarian Res. 2023;16(1):216. pmid:37968684 - 52.
Nasiri M, Monazzami A, Alavimilani S, Asemi Z. The impact of excessive depth intermittent and mixed (resistant and endurance) trainings on some anthropometric indices and cardio efficiency in ladies with polycystic ovary syndrome: a randomized managed scientific trial research. Int J Fertil Steril. 2022;16(4):268–74. pmid:36273312 - 53.
Kabiri SS, Javanbakht Z, Zangeneh M, Moludi J, Saber A, Salimi Y, et al. The results of MIND weight loss program on melancholy, nervousness, high quality of life and metabolic and hormonal standing in overweight or obese ladies with polycystic ovary syndrome: a randomised scientific trial. Br J Nutr. 2026;135(5):496–509. pmid:39465581 - 54.
Tripathi PP. Effect of wolly exercise in PCOS and PCOD sufferers as a part of administration. SSR-IIJLS. 2023;9(4):3281–9. - 55.
Niranjani S, Bhuvaneswari G, Hemamalini M, Vijayalakshmi R. Efficacy of cinnamon, train and counselling (multi-interventional Package) on insulin resistance amongst younger ladies with Polycystic Ovarian Syndrome. J Pharm Negat Results. 2022;13(Special Issue 9):2463–8. - 56.
Souza PD, Rodrigues DE, Kaipangala RG, Leena KC. Effectiveness of multimodular interventions of way of life modification on signs of polycystic ovarian syndrome and high quality of life amongst ladies: a quasi-experimental research. J Clin Diagn Res 2022. - 57.
Meenakshi M, Anitha A, Ramana Ok, Kamalakannan M. Efficacy of Swiss ball train and resistance coaching in polycystic ovarian syndrome. IJPOT. 2024;18:302–9. - 58.
Dietz de Loos A, Jiskoot G, Louwers Y, Beerthuizen A, Busschbach J, Laven J. Pregnancy outcomes in ladies with PCOS: follow-up research of a randomized managed three-component way of life intervention. J Clin Med. 2023;12(2):426. pmid:36675355 - 59.
Kim C-H, Lee S-H. Effectiveness of way of life modification in polycystic ovary syndrome sufferers with weight problems: a scientific assessment and meta-analysis. Life (Basel). 2022;12(2):308. pmid:35207595 - 60.
Gautam R, Maan P, Jyoti A, Kumar A, Malhotra N, Arora T. The function of way of life interventions in PCOS administration: a scientific assessment. Nutrients. 2025;17(2):310. pmid:39861440 - 61.
Aerobic Exercise and Weight Loss in Adults: A Systematic Review and Dose-Response Meta-Analysis | Nutrition, Obesity, Exercise | JAMA Network Open | JAMA Network. n.d. [cited 2026 April 1]. Available from: - 62.
Guastella E, Longo RA, Carmina E. Clinical and endocrine traits of the primary polycystic ovary syndrome phenotypes. Fertil Steril. 2010;94(6):2197–201. pmid:20303485 - 63.
Unfer V, Kandaraki E, Pkhaladze L, Roseff S, Vazquez-Levin MH, Laganà AS, et al. When one dimension doesn’t match all: reconsidering PCOS etiology, prognosis, scientific subgroups, and subgroup-specific therapies. Endocr Metab Sci 2024;14:100159.
This web page was created programmatically, to learn the article in its authentic location you’ll be able to go to the hyperlink bellow:
https://journals.plos.org/plosmedicine/article%3Fid%3D10.1371/journal.pmed.1004887
and if you wish to take away this text from our website please contact us


